'Strong Hair-Loss Drug' Era Draws to a Close, Giving Way to Personalized, Low-Dose Hair-Loss Treatment... A New Paradigm for Hair-Loss Treatment [Hong Ju-hyeong's Introduction to Hair Science]
- Input
- 2026-11-22 06:00:00
- Updated
- 2026-11-22 06:00:05
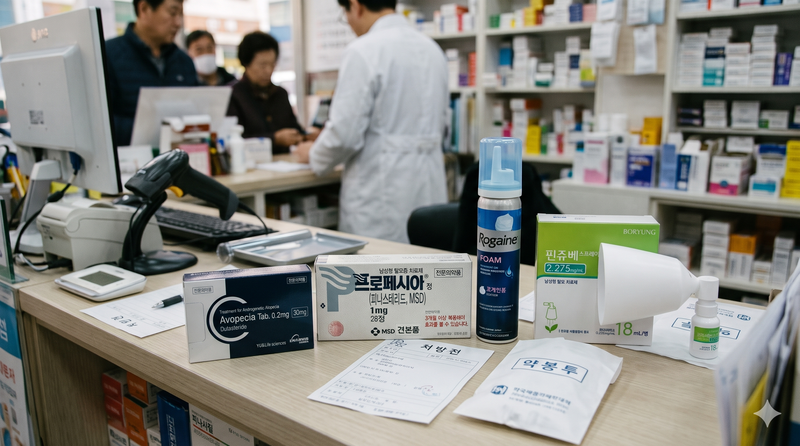
[Financial News] Prescribing hair-loss medication, once limited to taking it “at a strong dose for a long time,” is evolving into a new paradigm of “personalized, low-dose, topical” treatment. The need for precise prescriptions tailored to patients’ risk profiles is growing, alongside multidimensional assessments of drug efficacy and side effects based on the latest clinical evidence.
You don’t have to take hair-loss medication “aggressively” and put up with side effects
For a long time, the basic formula for prescribing hair-loss medication was relatively simple. Once a patient was diagnosed with male-pattern hair loss, the standard approach was to have them take a fixed daily dose of a 5-alpha-reductase inhibitor such as finasteride or dutasteride. But the paradigm for hair-loss treatment now observed in clinical practice is clearly moving away from the “strong and long-term” approach, toward lower doses and topical treatments tailored to each patient.
This shift stems from the accumulation of recent clinical data and a growing demand for greater precision in assessing safety. In terms of efficacy, network meta-analyses and randomized controlled studies have repeatedly reported that dutasteride 0.5 mg produces a greater increase in hair count than finasteride 1 mg. A recent domestic multicenter study also demonstrated that low-dose dutasteride 0.2 mg has a therapeutic effect comparable to that of 0.5 mg, opening up the possibility of optimizing dosage.
If you’re uncomfortable with oral hair-loss medication, spraying it on is another option
On the safety front, warnings about mood-related adverse reactions to finasteride, including suicidal thoughts, have been added to official labeling, and regulatory authorities have stepped up monitoring. This has increased clinical demand for reducing systemic exposure to the drug. Standardized topical finasteride, which has demonstrated efficacy while lowering systemic absorption, is emerging as an alternative.
An evidence-based perspective is also taking shape on prescriptions for generics (copycat drugs), which make up a large part of the market. Domestic generics approved after passing bioequivalence (BE) tests meet the standards for blood exposure (AUC) and peak concentration (Cmax), and are recognized as therapeutically equivalent. However, the fact that differences in absorption due to variations in excipients and coatings may lead to differences in how patients respond has also become a consideration in personalized prescribing.
Designing an initial treatment plan for each patient through rigorous screening... the path to combination therapy
Under the new paradigm, hair-loss medication should not be prescribed mechanically; the decision should come only after a thorough analysis of the patient’s multiple risk factors.
First, screen thoroughly for underlying conditions and medical history. Check for a history of mood disorders such as depression or anxiety, liver dysfunction, and family-planning intentions. For women, contraindications related to pregnancy and breastfeeding must also be checked. In particular, 5-alpha-reductase inhibitors lower prostate-specific antigen (PSA) levels, so PSA readings must be adjusted accordingly during prostate screening.
Second, design the initial treatment plan to reflect the patient’s hair-loss pattern and psychological sensitivity. Assess the rate of progression and family history, and separately evaluate the pattern of hair loss at the crown and front of the scalp to choose the more appropriate ingredient, finasteride or dutasteride. For patients particularly anxious about side effects, the strategy may be to start with a low dose and increase it gradually. Alternatively, thorough counseling beforehand can help prevent a nocebo effect caused by psychological factors and improve medication adherence during the first 1–3 months.
Third, combine treatments and correct imbalances in the body’s internal environment. Hair-loss medication must be taken consistently for at least 6–12 months to produce meaningful changes; if treatment is stopped, the condition, which is chronic in nature, gradually progresses again. An integrated approach is therefore needed: combine oral and topical minoxidil with standardized topical formulations, and use blood tests to identify and correct vitamin D deficiency, low ferritin (iron stores)—common in female patients—and imbalances in trace elements such as zinc.
Hair-loss treatment is more than simply prescribing medication; it is a process of precise treatment planning that seeks the optimal balance of efficacy and safety in light of the patient’s lifestyle and risk of side effects.

/Hong Ju-hyeong, director of Moheel Clinic
[email protected] Kim Hyeon-seon Reporter